
Spinal cord stimulation (SCS) is a proven method for treating chronic pain. It is considered when other treatments—such as physical therapy, medication, or even surgery—have not provided the desired pain relief. The principle behind it: A small stimulator delivers targeted electrical impulses via fine electrodes placed near the spinal cord. These impulses stimulate pain-inhibiting nerve pathways and block pain signals before they are perceived. The treatment can significantly reduce chronic pain and improve quality of life in everyday activities.
When is spinal cord stimulation used?
At Inselspital, we use spinal cord stimulation to treat the following medical conditions:
- Persistent Spinal Pain Syndrome
- Back and/or leg pain without prior surgery
- Complex regional pain syndrome
- Peripheral arterial occlusive disease
- Angina pectoris
Who is a candidate for spinal cord stimulation?
This procedure is primarily intended for patients for whom conservative, pharmacological, and surgical treatments have already been exhausted without providing the desired relief. As a result, these patients experience a significant reduction in their quality of life and considerable distress.
To ensure that spinal cord stimulation is the right choice, a thorough evaluation by an interdisciplinary team is conducted first: specialists in pain management, psychiatry, and neurosurgery work together to determine whether the procedure is appropriate for each individual case. This approach ensures that every patient receives a treatment recommendation tailored to their personal situation.
How does spinal cord stimulation work?
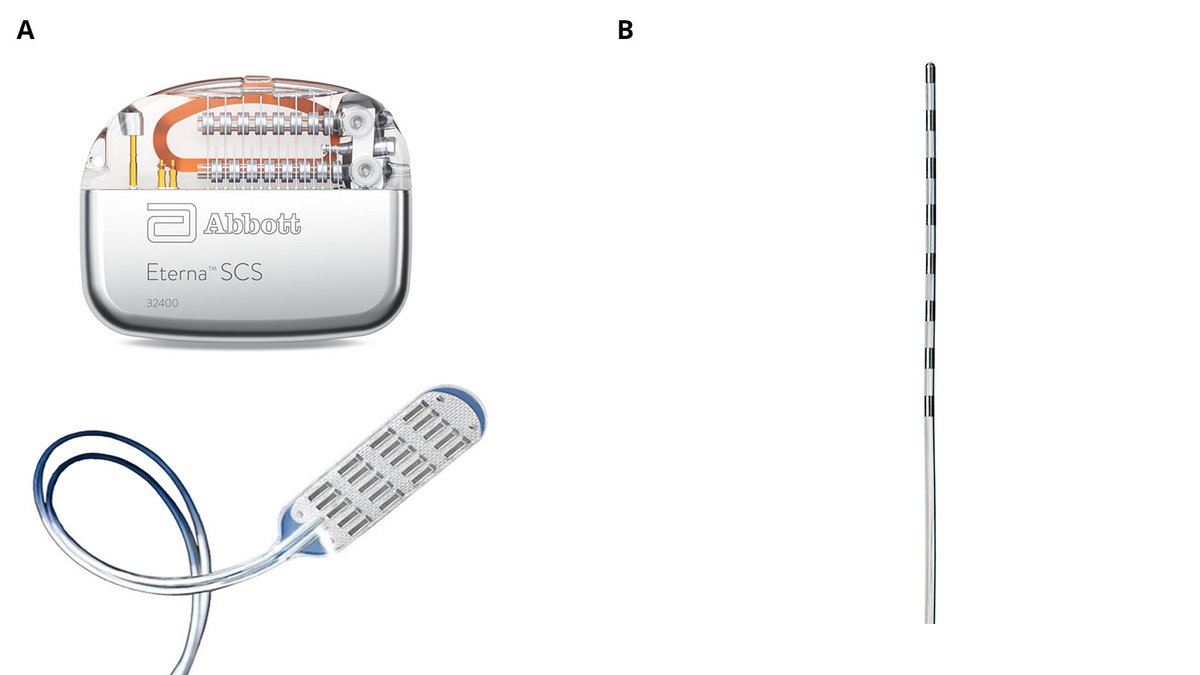
A spinal cord stimulation system consists of two main components: a neurostimulator and fine electrodes.
The neurostimulator is a small device that is implanted under the skin and generates targeted electrical impulses. It is connected via a fine cable to the electrodes, which are precisely placed in the area of the spinal cord during a minimally invasive procedure. These rod or plate electrodes deliver the impulses directly to the nerve tissue. There, they alter the transmission and processing of pain signals, which significantly alleviates symptoms.
While tonic stimulation was primarily used in the past—in which a noticeable tingling sensation (paresthesia) masked the pain—we now primarily use paresthesia-free methods. These operate below the threshold of perception and relieve pain completely without any tingling sensations.
What is the goal of spinal cord stimulation?
The primary goal is to improve quality of life. This includes:
- Reduction in pain of approximately 50%
- Reduction of pain medication
- Improvement in sleep quality
- Increase in physical activity
- Reintegration into the work process
- General improvement in psychological well-being
Although complete freedom from pain can be achieved in rare cases, it is not a realistic treatment goal of spinal cord stimulation. Rather, the primary focus is on a noticeable reduction in pain: This enables patients to lead more active daily lives, become more physically resilient, and improve their quality of life in the long term.

How does the implantation process work?
Patients who are candidates for spinal cord stimulation first undergo a trial period before the neurostimulator is permanently implanted.
Before surgery
- Imaging (MRI): As a standard procedure, an MRI of the thoracic and lumbar spine is performed. For procedures involving the cervical spine (cervical stimulation), an additional MRI of the cervical spine is required.
- Anesthesia: A consultation will take place in advance at our anesthesia clinic.
- System selection: Together, we will discuss whether an MRI-compatible and rechargeable system is the best choice.
Day of surgery
Patients are admitted to the hospital the day before surgery. Today, the procedure is almost always performed under general anesthesia. Intraoperative monitoring ensures that the electrodes provide optimal coverage of the painful area. Only in exceptional cases—when this monitoring cannot be used—is the surgery performed under local anesthesia. In this case, patients are awake during the procedure and provide direct feedback on whether the painful area is being adequately covered.
In the operating room, the neurosurgeon places the electrodes precisely on the spinal cord under X-ray guidance. Once at least 80% of the affected area is covered, the electrodes are connected to an extension under the skin and routed outward to the torso. An external test stimulator is then connected to this. For monitoring purposes, patients stay in the hospital overnight and can return home the following day.
During the test period
The test periodlasts one to two weeks. During this time, showering or bathing is not permitted. Spitex will arrange for care to ensure regular wound checks and dressing changes.
Definitive implantation
If the trial phase is successful, the permanent implantation of the neurostimulator (often colloquially referred to as a «battery») is performed on an outpatient basis: The patient arrives in the morning for the procedure and can return home that same evening.
If, on the other hand, the patient does not respond adequately to the stimulation, the electrodes can be easily removed.
Aftercare
The patient returns to our clinic after 2 weeks for a wound checkup. During this visit, the stimulator is checked and the stimulation is adjusted if necessary. Regular checkups take place after 6 weeks, 3, 6, and 12 months, and then annually. When the neurostimulator’s battery runs out, it must be replaced through a minor procedure performed under local anesthesia.
What are the complications?
The complication rate is low. However, as with any procedure, complications can occur.
In the early phase
- Bleeding, which can lead to temporary or, rarely, permanent paralysis and require surgical relief
- Infections during the test phase
- Electrode displacements
- Connection problems of the electrodes with the battery
- Battery malfunctions
In the late phase
- Loss of effect of stimulation
- Infections
- Electrode displacement
- Electrode breakage
- Cable breakage
- Battery malfunctions
- Pain in the area of the battery pocket
What are the chances of success?
The success rate of spinal cord stimulation varies depending on the clinical picture and the patient population. Over the long term, approximately 70 to 80 % of patients achieve clinically significant pain relief. The earlier the procedure is used in the course of the disease, the higher the chances of success. Progressive chronicity has an adverse effect on the response.
In some patients (approximately 13 to 26 %, depending on the duration of observation), a loss of efficacy may occur over time, a phenomenon known as habituation (the habituation effect). In such cases, switching to a different stimulation method often restores very good pain relief.
-
Patil AS, Levasseur B, Gupta M. Neuromodulation and Habituation: A Literature Review and Conceptional Analysis of Sustaining Therapeutic Efficacy and Mitigating Habituation. Biomedicines. 2024 Apr 23;12(5):930. doi: 10.3390/biomedicines12050930.
-
Deer T, Slavin KV, Amirdelfan K, North RB, et al. Success Using Neuromodulation With BURST (SUNBURST) Study: Results From a Prospective, Randomized Controlled Trial Using a Novel Burst Waveform. Neuromodulation. 2018 Jan;21(1):56-66. doi: 10.1111/ner.12698. Epub 2017 Sep 29.
-
De Ridder D, Lenders MW, De Vos CC, Dijkstra-Scholten C, Wolters R, Vancamp T, Van Looy P, Van Havenbergh T, Vanneste S. A 2-center comparative study on tonic versus burst spinal cord stimulation: amount of responders and amount of pain suppression. Clin J Pain. 2015 May;31(5):433-7. doi: 10.1097/AJP.0000000000000129.
-
Deer T, Gilligan C, Falowski S, et al. Treatment of Refractory Low Back Pain Using Passive Recharge Burst in Patients Without Options for Corrective Surgery: Findings and Results From the DISTINCT Study, a Prospective Randomized Multicenter Controlled Trial. Neuromodulation. 2023 Oct;26(7):1387-1399. doi: 10.1016/j.neurom.2023.07.009. Epub 2023 Aug 28.
-
Falowski S, DeRidder D. BurstDR and multi-area Burst DR spinal cord stimulation for the treatment of chronic pain: "less is more". Pain Manag. 2026 Jul;16(7):721-735. doi: 10.1080/17581869.2026.2663948. Epub 2026 Apr 30.